Women with gluteal tendinopathy are seeing real change in pain they were told was “just bursitis”.




For as long as most women can remember, gluteal tendinopathy — the burning pain on the outside of the hip — has been explained with one wrong word: bursitis.
“Just bursitis.” “Take an anti-inflammatory.” “Let’s do another shot.” “You may have to learn to live with it.” The same short list of answers, handed to millions of women who can no longer lie on their side at night — all of them built on one assumption: that if the outer hip hurts, the problem must be an inflamed little sac of fluid, and the only real fix is to calm it down again, and again.
But that never explained why the shot wears off after a few weeks. Why the X-ray comes back “clean.” Why two women with the same diagnosis live completely different lives — one walks the dog every morning, the other dreads the moment she turns onto her side in bed. Something else has to be going on.
Researchers have been looking at that “something else” for over a decade.
And what they found usually isn’t the bursa at all. It is the tendons of the muscles that are supposed to hold the hip steady — squeezed against the bone because the muscles above them have quietly stopped doing their job. It was never visible on an X-ray, because an X-ray was never designed to show a tendon, or whether a muscle is switching on.
Once that is understood, gluteal tendinopathy stops looking like an inflammation that simply keeps flaring — and starts looking like something with a real cause, and a real path forward.

What the Research Actually Found
There is a reason the X-ray never explained the pain — and it is not the reason women were given.
An X-ray looks at bone. It shows the hip joint, the ball and the socket. It comes back “clean.” That is all it was built to do.
It was never built to show the tendons on the side of the hip — or whether the muscles above them are still firing.
Most women with gluteal tendinopathy have already been told what’s wrong. That it’s inflamed. That it flares lying on that side, after a walk, getting out of the car. That it’s worse at night and by late afternoon.
All of that is true.
Read that again: even the hip that doesn’t hurt is weaker. The weakness came first. The pain came after.
What nobody told them is what that weakness does. Why it hurts most lying on that side. Why a short walk now sets it off. Why the burning spreads down the outside of the thigh.
The answer is a muscle called the gluteus medius — the fan-shaped stabilizer on the outside of the hip.
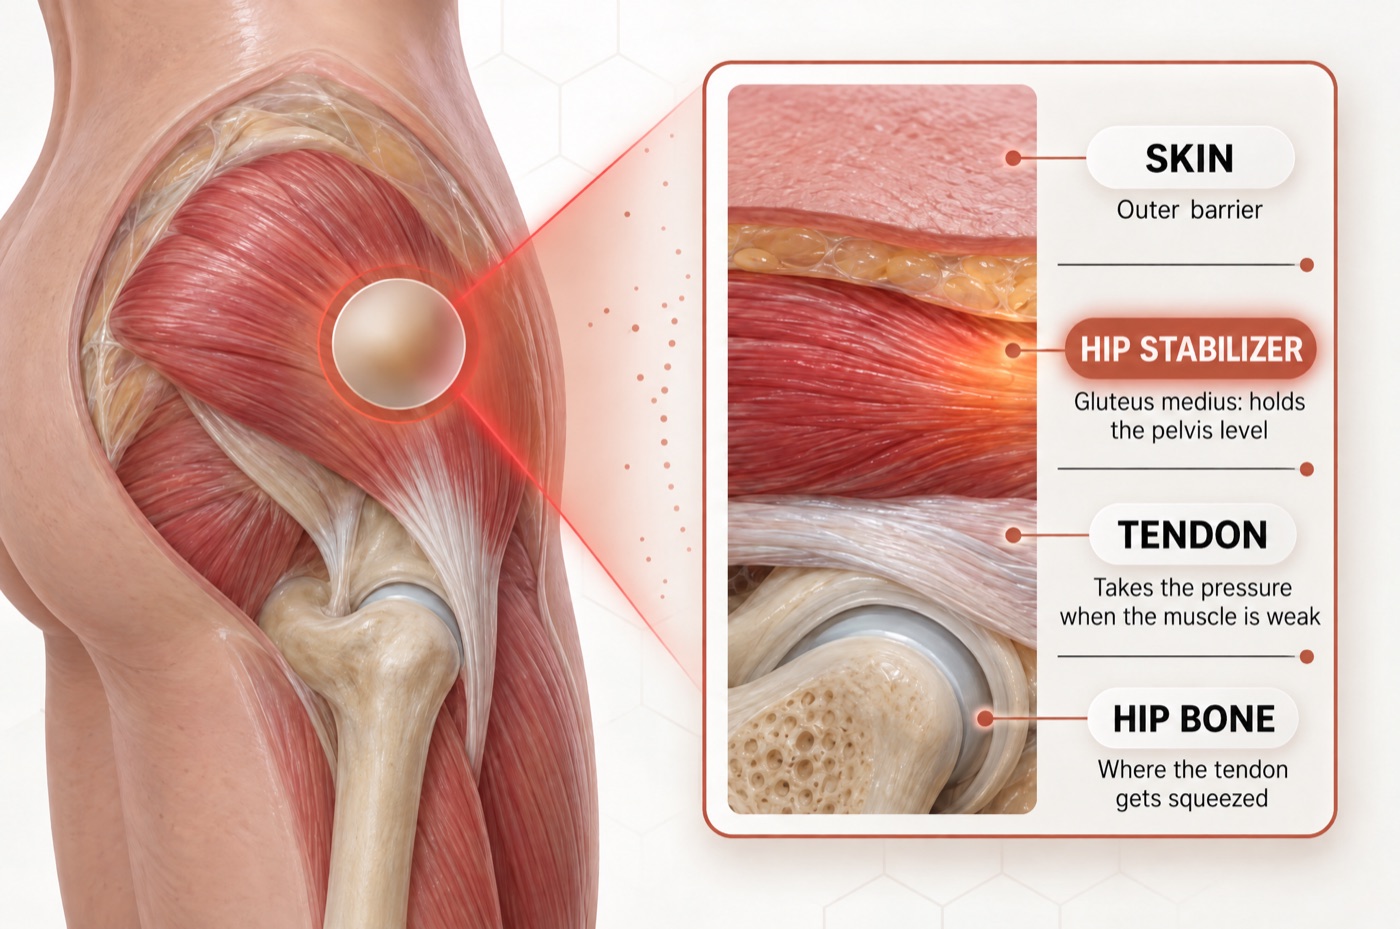
Every time one foot leaves the ground, this muscle fires on the other side and holds the pelvis level. Thousands of times a day. On every step, every stair, every time you stand up. In a healthy body it works so quietly that nobody ever thinks about it. It is invisible by design.
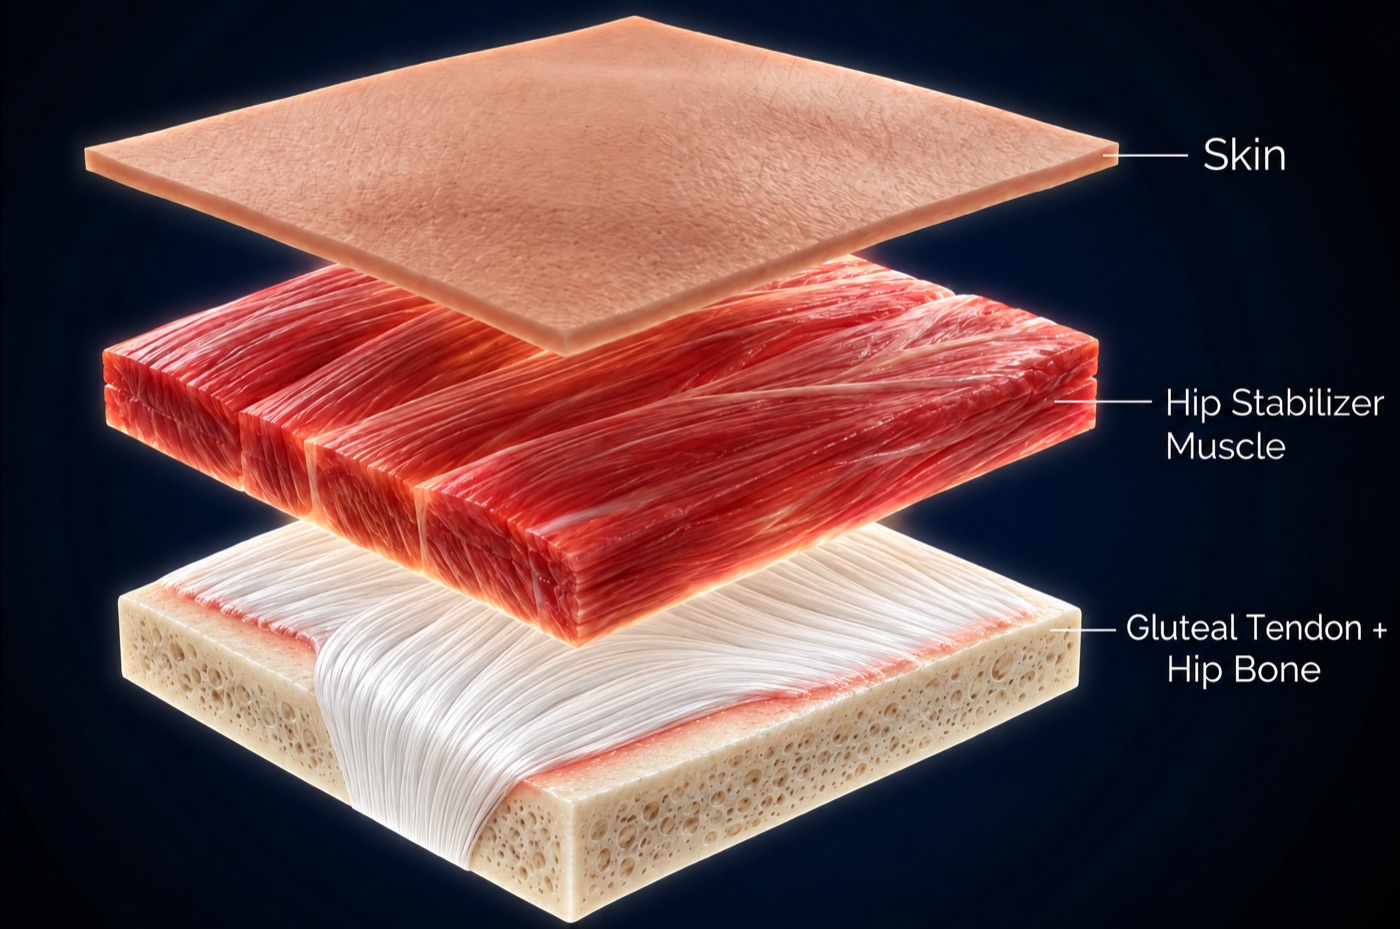
And it is usually the first muscle to lose strength. Around menopause, as estrogen falls, muscle starts losing strength a little every year — and the first to go are the muscles that carry the most weight for their size. This one holds up the whole pelvis on one leg, thousands of times a day, and nothing in normal life ever trains it. It weakens quietly, with no pain at all. The pelvis starts to drop a little on every step, and the tendon underneath starts getting squeezed against the bone. That is when the burning begins.
From there, two things about this muscle matter more for gluteal tendinopathy than anything else.
First: when the outer hip hurts, the nervous system turns this muscle down. It is a protective reflex — the muscle that should be taking the strain stops receiving the full command to fire.

Second: a muscle that doesn’t fire doesn’t stay the same. It shrinks. And when the stabilizer shrinks, the tendons underneath it take the load — pressed against the bony point of the hip on every single step.
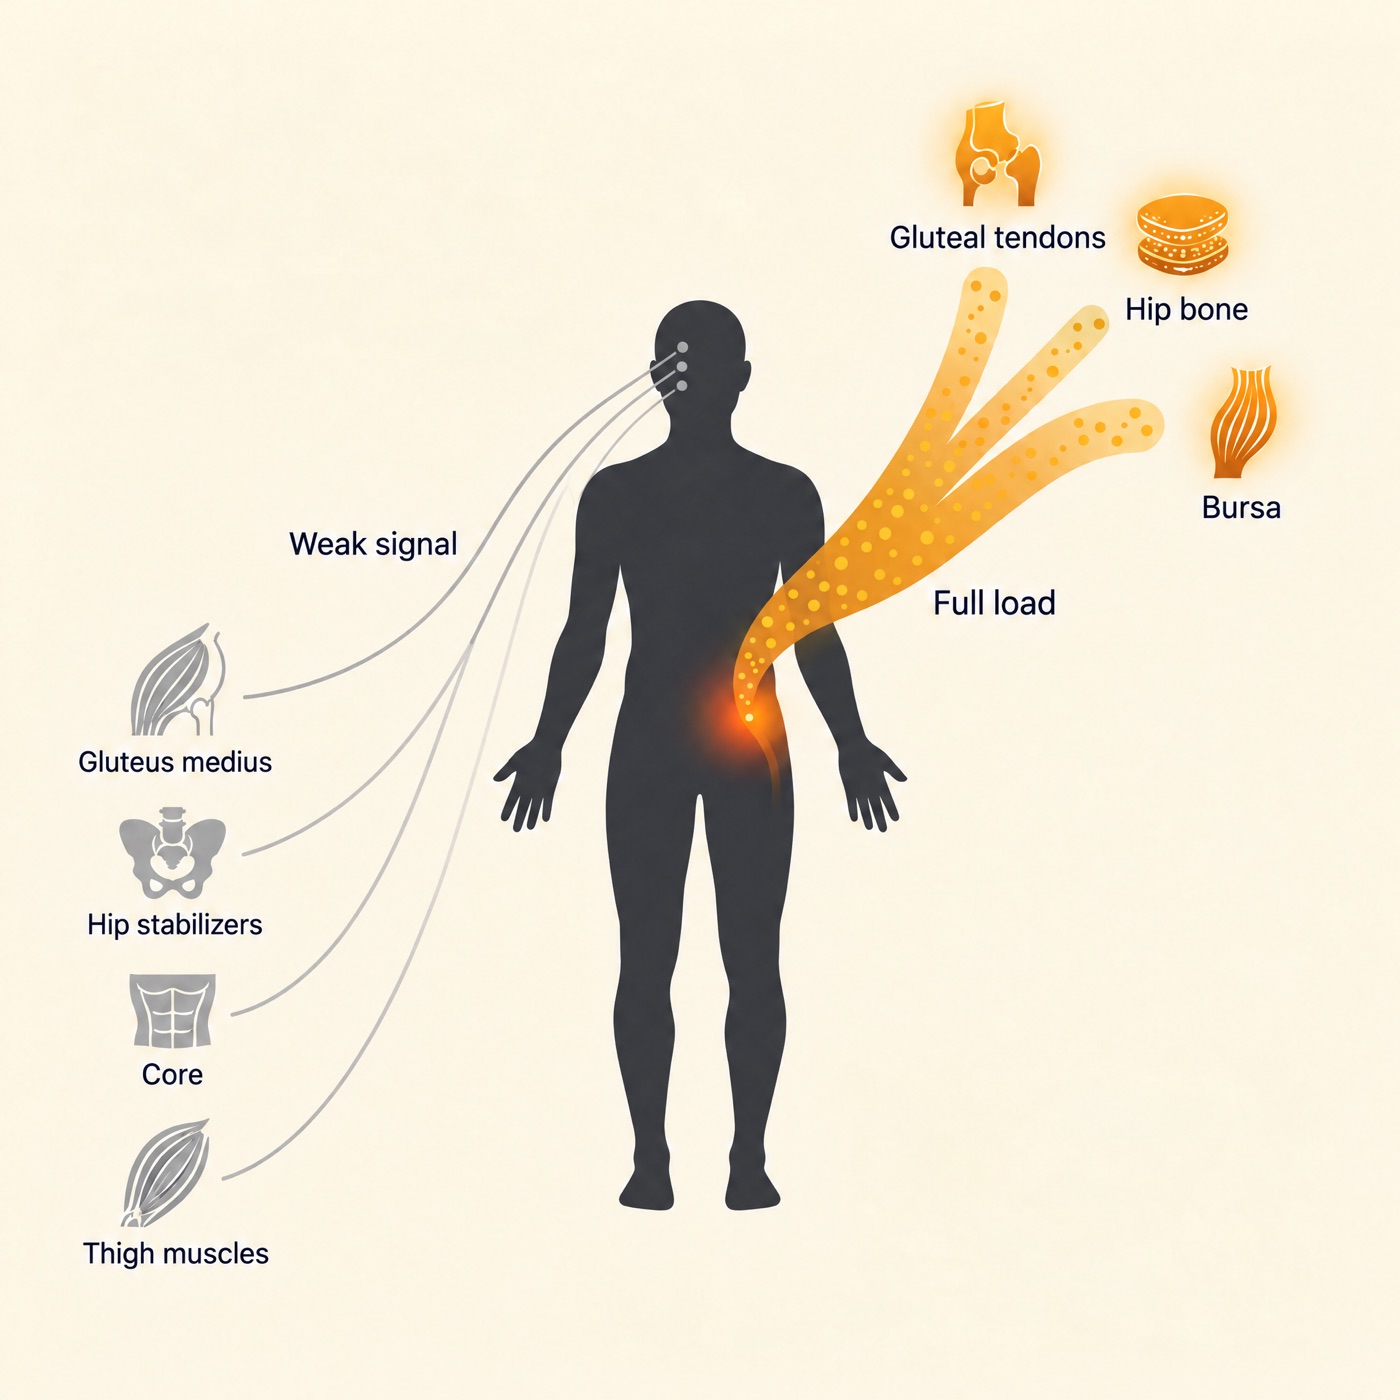
And that is where the circle closes.
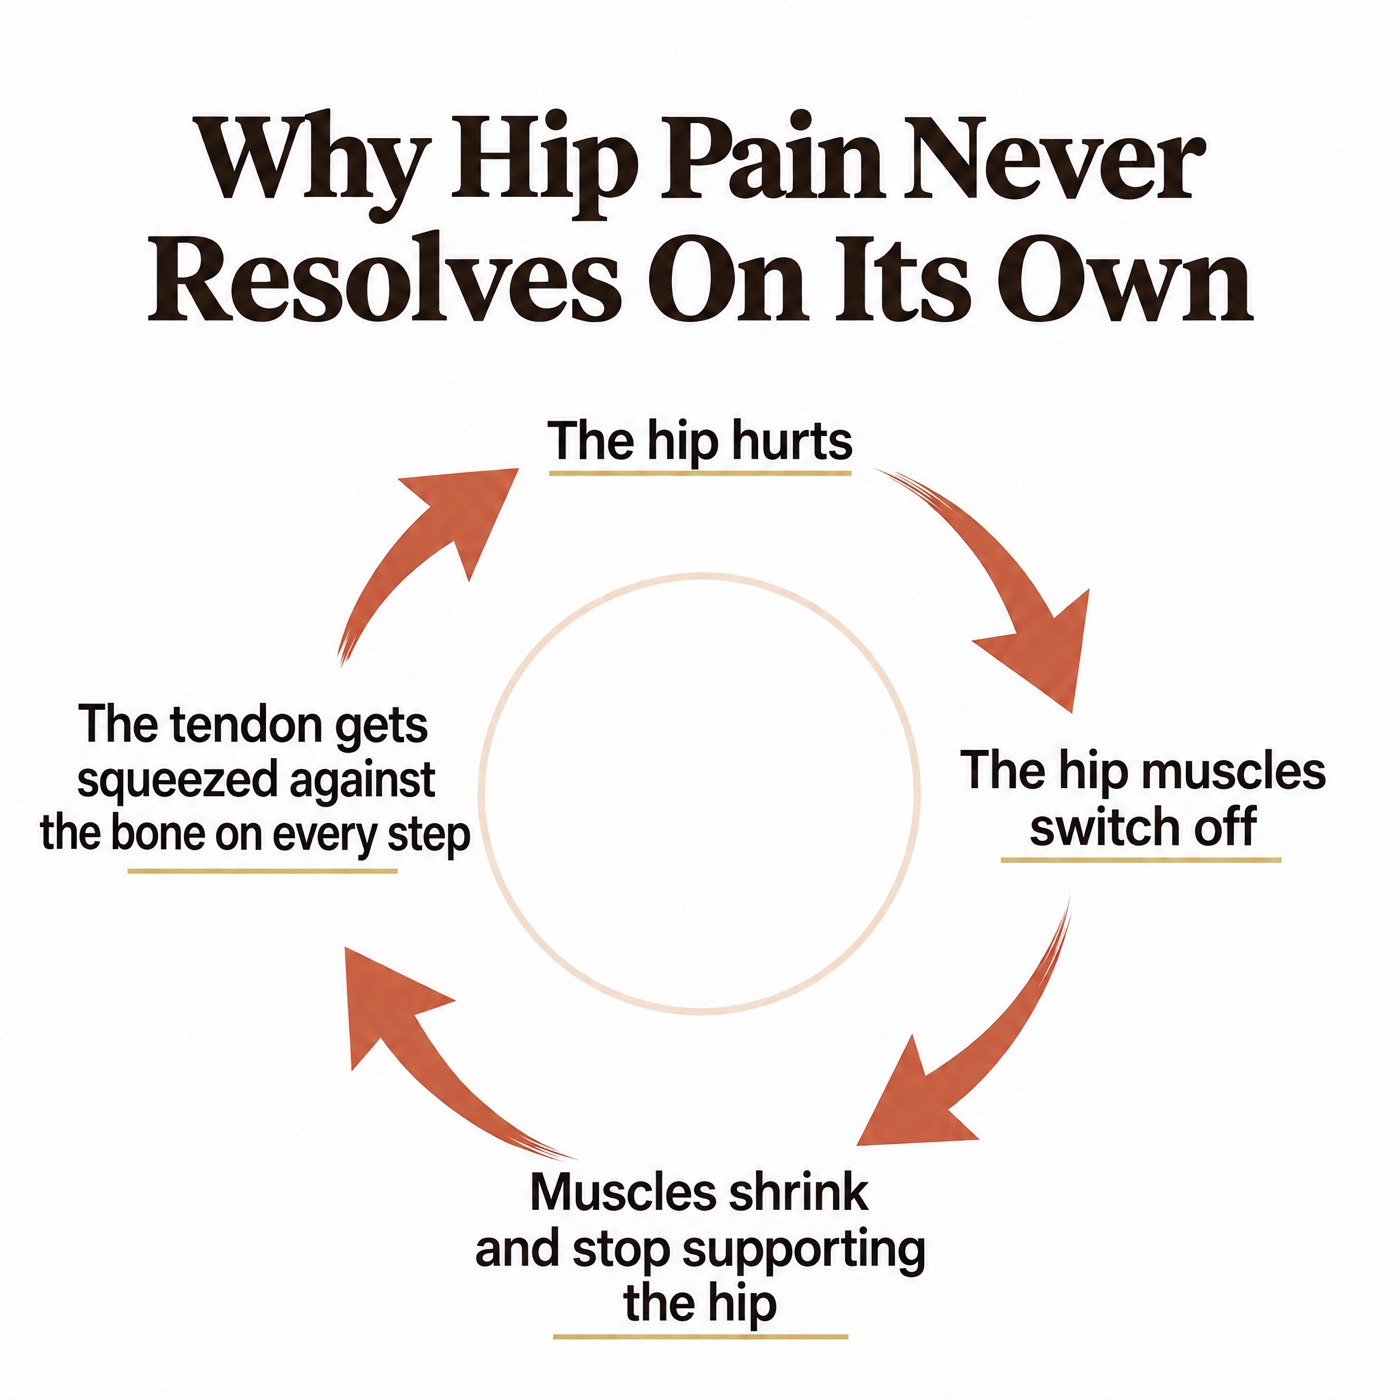
The hip hurts, so the muscle switches down. The muscle switches down, so the tendon takes more load. The tendon takes more load — squeezed against the bone — so it hurts more. Month by month, the muscles that should be holding you up go quiet — and the pain gets worse for a reason no X-ray will ever show.
Researchers call it a Core Muscle Lockout. Menopause lit the match. The lockout is the fire. The stabilizers aren’t gone. They are locked out — still there, still able to work, but no longer answering on their own.
Why Every Symptom Finally Makes Sense
Once the lockout is understood, every symptom of gluteal tendinopathy — the ones that seemed random, the ones you were told are just bursitis — starts to fit together. Not as a list of unrelated problems. As one problem, showing up in a dozen places.
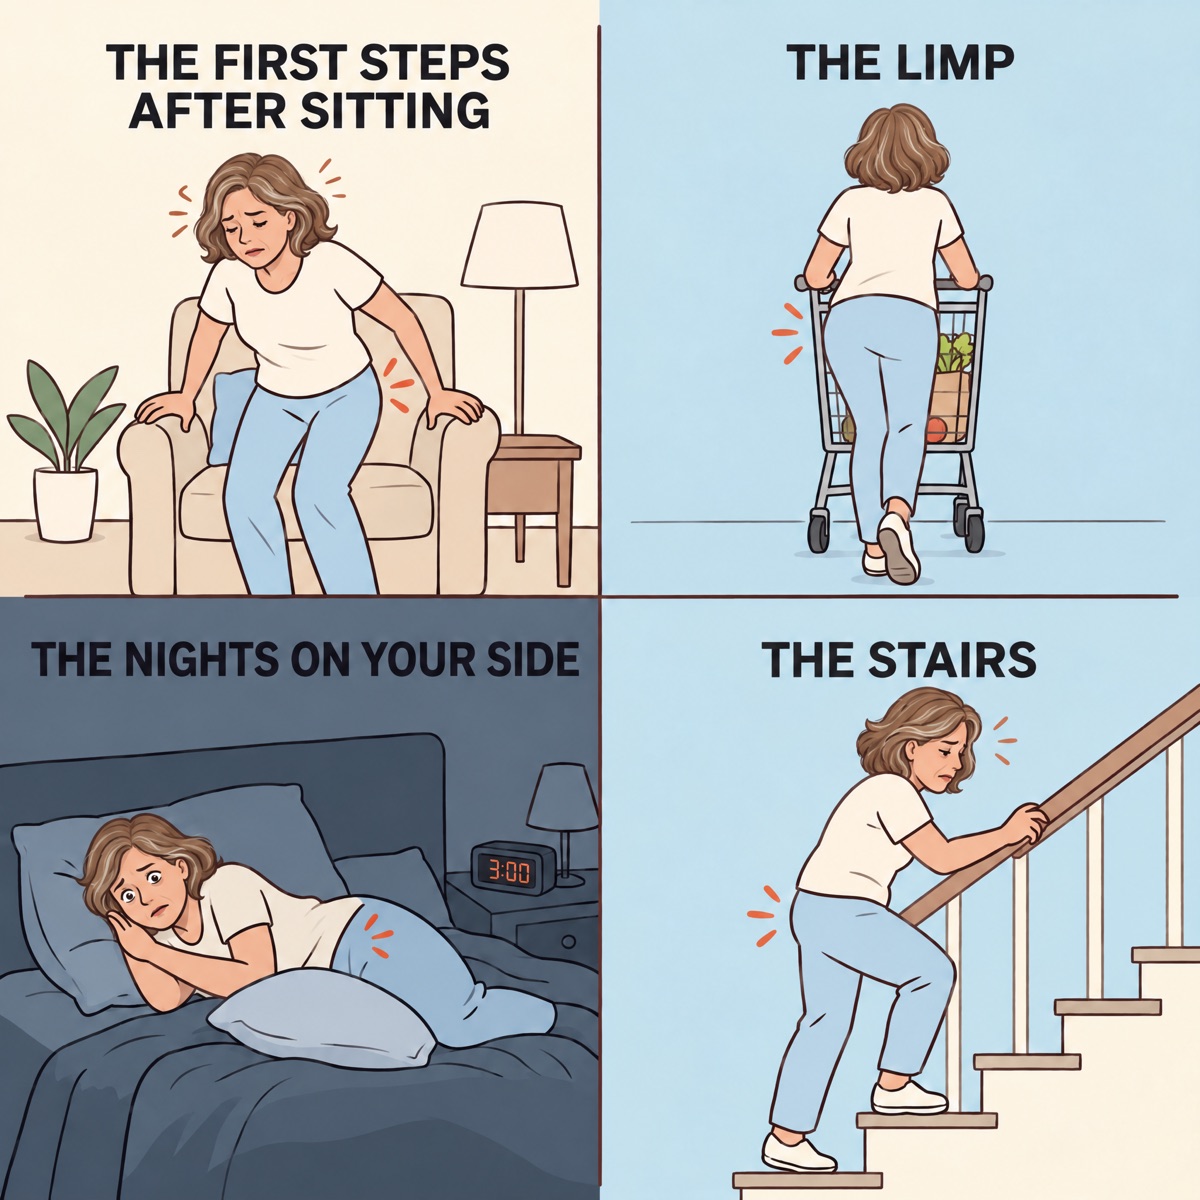
Sitting low or crossing your legs bends the tendon tight over the bony point of the hip. When you stand, the stabilizer is supposed to switch on before you even move. In a locked-out hip, it switches on late — or barely at all. So the tendon takes the strain alone.
The gluteus medius keeps the pelvis level on every step. When it stops firing, the pelvis drops and the hip swings out to the side — and that swing presses the tendon even harder against the bone, step after step.
Lying on your side presses the bony point of the hip into the mattress — right where the tendons of the quiet muscles attach. Lying on the other side, the top leg drops and stretches the same tendons tight.
Every stair — every leg into your pants — is a moment on one leg. With the stabilizer locked out, the tendon carries the whole body on its own — and the back and knee start paying for it too.
For years, women with gluteal tendinopathy have been told it’s bursitis. Told to take the pills, get the shot, do the clamshells, and learn to live with it. Told the clean X-ray means nothing serious is wrong — while nobody checked whether the muscles were still working.
Now every symptom above is explained by the same finding — the muscles that hold the hip steady, locked out and shrinking.
Not a mystery. Not “just bursitis.” Not something you have to learn to live with.
One group of muscles, in one state, producing everything you have been living with — and everything you have been trying to explain to the people around you — for years.
Why Nothing on the Standard Shelf Has Ever Lasted
Most women who have had gluteal tendinopathy for any length of time have cycled through the standard shelf.
Advil, morning and night. Tylenol. Voltaren gel. A TENS unit from the pharmacy. The cortisone shot — then the second, then the third, until the doctor says no more. A physical therapy sheet of clamshells and bridges. A pillow between the knees at night. A menopause supplement, collagen powder, a red light wrap. And the PRP quote, two thousand dollars, “not covered by insurance.”
And every one comes with the same pattern. A few good weeks. Then it wears off, and back to where things started.
The reason is simple: almost every one of them works on the pain signal.
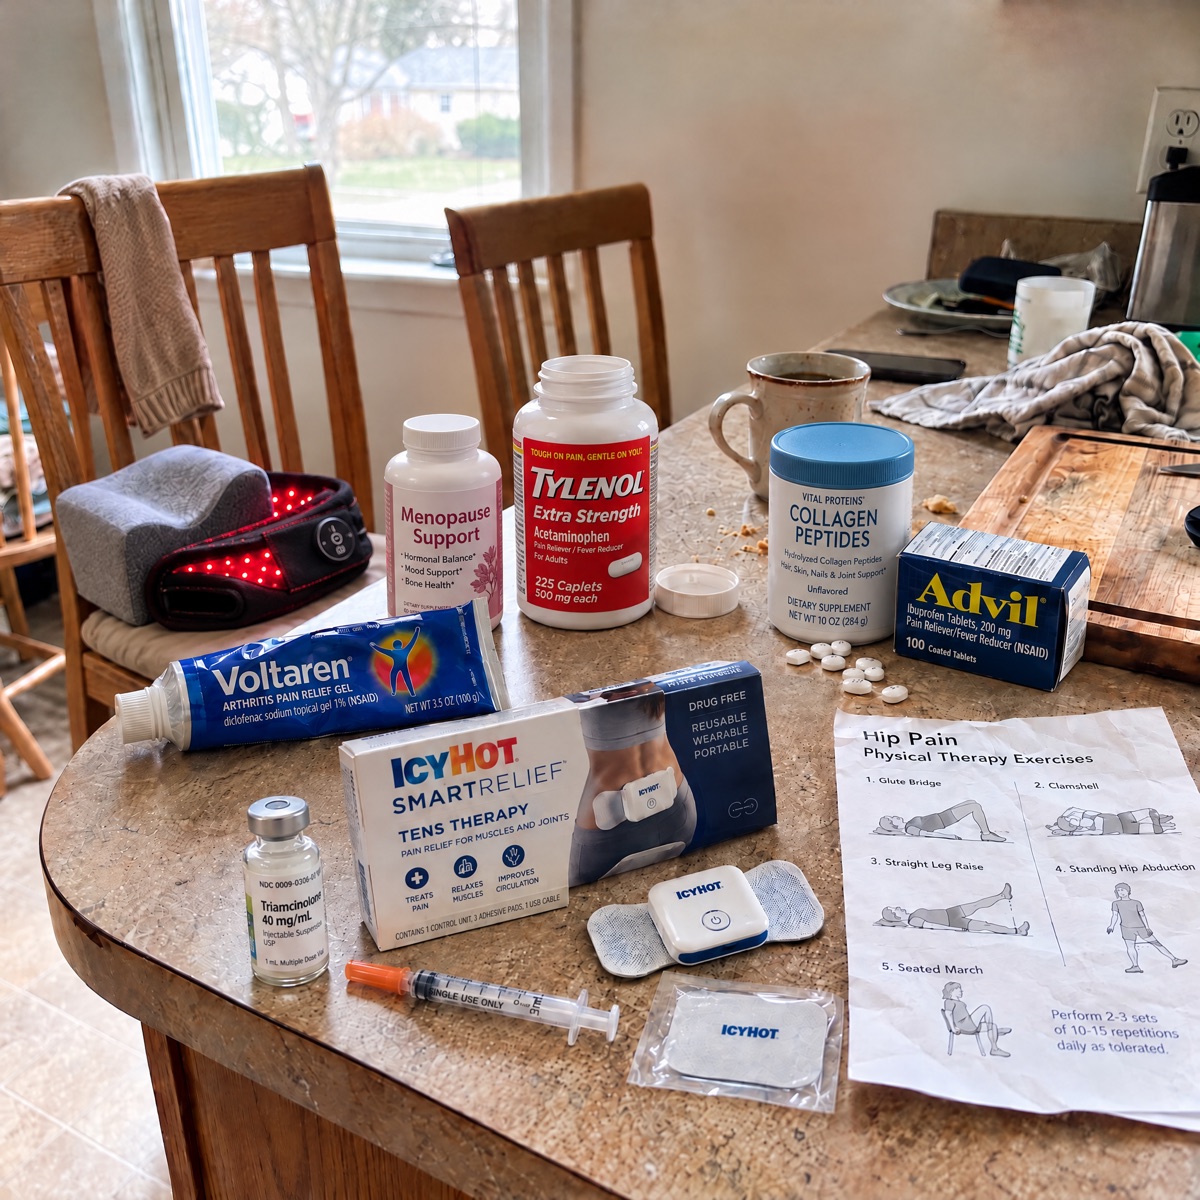
Pills and gels dull the pain. A TENS unit buzzes over the nerve to mask the signal. The shot calms the inflammation for a few weeks. None of them make a locked-out muscle fire. Physical therapy is the one thing aimed at the muscles — but clamshells and leg stretches press the tendon against the bone, which is why so many women find they make it worse, and when the visits end, the exercises usually end too. And a PRP shot is aimed at the tendon; it doesn’t switch the muscles back on. The supplements and the red light feed the tendon or warm the skin — none of them makes a locked-out muscle fire.
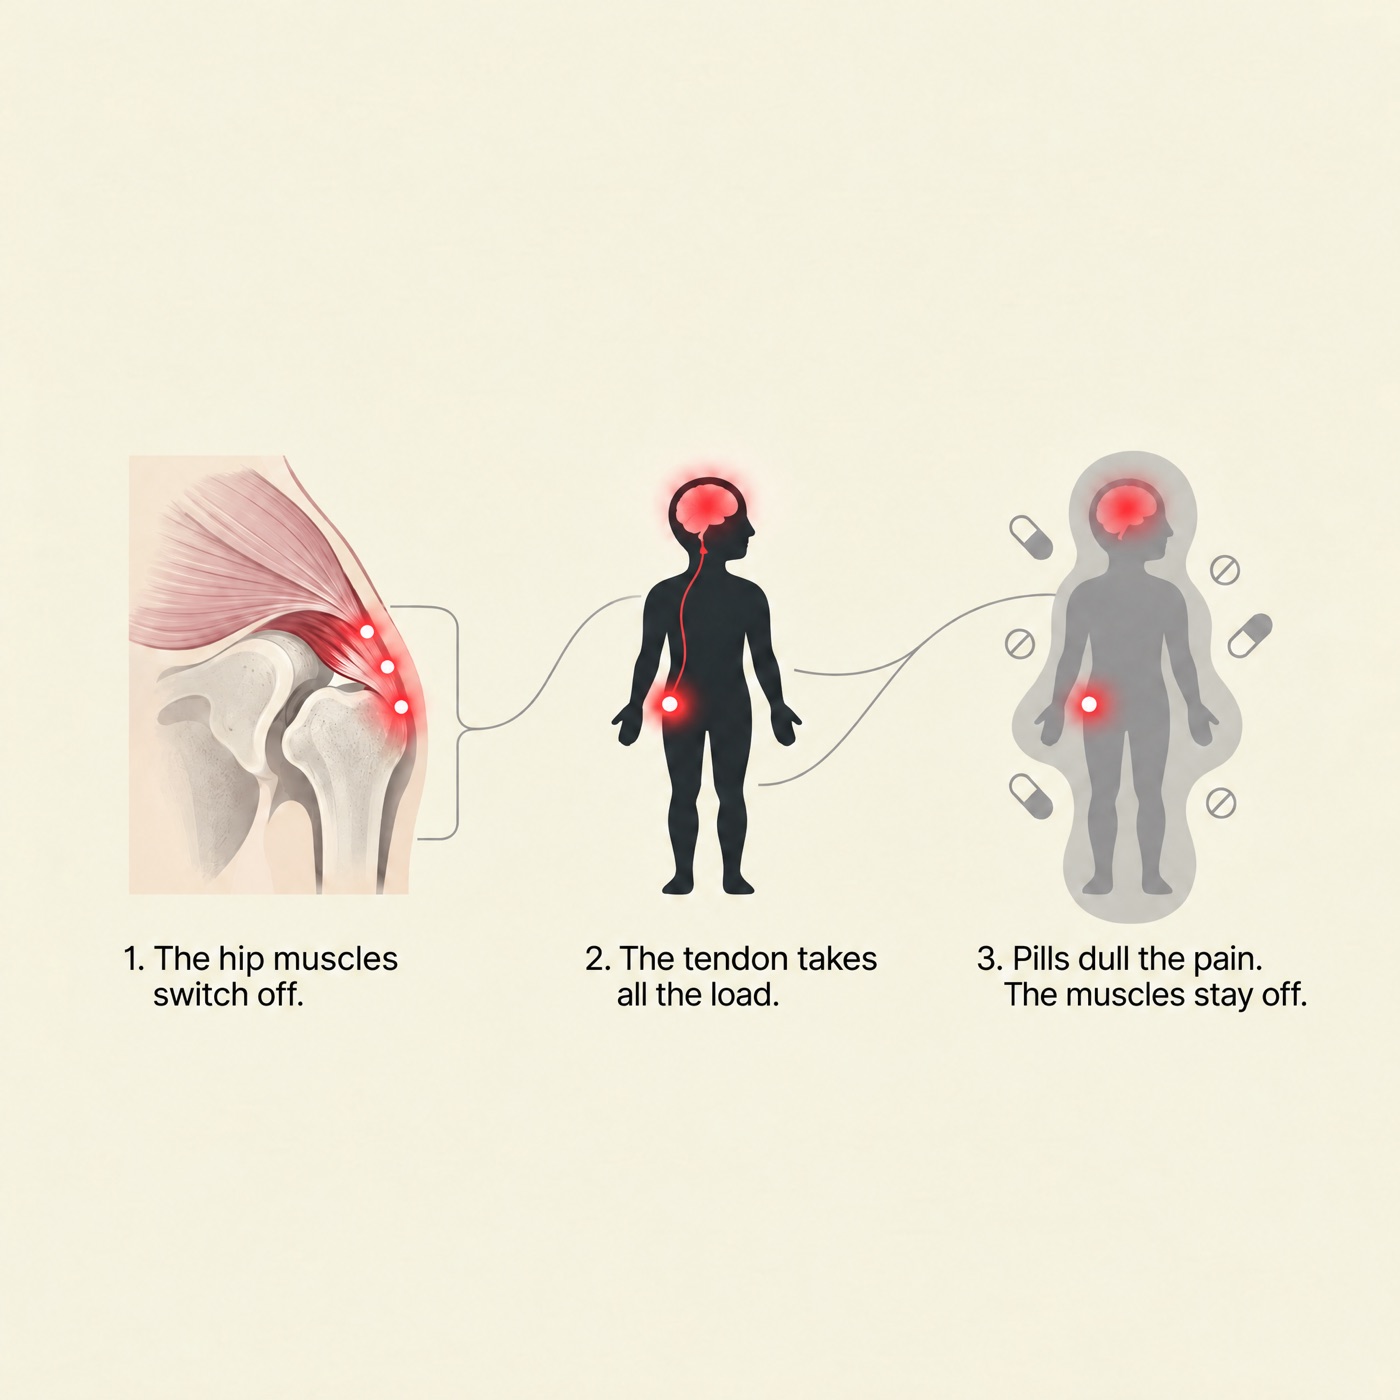
It is like painting over a crack in the wall, and never once looking at the foundation.
What Finally Reaches the Real Problem
Which raised the obvious question.
If the stabilizers are locked out — and if almost nothing on the shelf is aimed at them — then the real answer is not another pill or another shot.
The real answer is to make those muscles contract again, every day, without squeezing the tendon underneath — until the connection between brain and muscle rebuilds and they start firing on their own.
The catch is in that word: working. A muscle that has been switched off doesn’t answer an exercise sheet — and the wrong exercise presses on the very tendon that hurts. It needs to be made to contract first, without loading the tendon — and without waiting for the brain to switch it back on.
That is exactly what neuromuscular electrical stimulation (NMES) does. It sends a gentle signal through the skin that makes the muscle itself contract — no movement, no weight on the hip. It has been used for decades in muscle rehabilitation and sports medicine. It is not a TENS: a TENS masks the pain signal, NMES makes the muscle work.
The problem: for most women, it only ever existed in a clinic.
The Turning Point Came in 2026
That is finally changing.
In 2025, a small team of physical therapists and device engineers kept running into the same patient. A woman in her late fifties, years of “bursitis” shots behind her — and outer hip muscles that simply would not switch on, no matter how many clamshells she did at home. The clamshells only made it worse.
The research had identified the muscles. The technology to make them contract already existed. Every piece was there.
And no one had put it together. Millions of women with gluteal tendinopathy, a documented lockout in the muscles above the tendon, and not one device made for them — because the stimulators on the market were built for backs, for knees, for athletes in a clinic, with wires everywhere and an app to pair. Nothing was made for a woman who wanted to sit in her own chair, put one pad on the outside of her hip, and press one button.
So rather than wait for someone else, they decided to build it.

They spent the better part of a year on it — the shape of the pad, so it sits right over the stabilizer on the outer hip; the work-and-rest rhythm of the stimulation; a remote with buttons big enough to press without reading glasses.
What came out of it is called CoreReset: an NMES device made specifically for the stabilizers on the outside of the hip.
The first units went to a group of women who had already tried everything on the shelf, and their progress was tracked over 90 days.
By day 90, the answers that came back changed how the team understood the lockout itself.

The Real-World Results
The first group was chosen deliberately: 1,084 women with gluteal tendinopathy, most of them first told it was bursitis, every one in pain for at least two years, every one having already worked through pills, cortisone shots and physical therapy — and every one told, at some point, that she would just have to live with it. Before the hip, every one of them had been some version of the same woman: the one who walked every morning, gardened all Saturday, danced at every wedding, and never once thought about which side she slept on. Over the first 90 days, they reported the following.
Every response came from a real woman filling out a form on her phone, in her own words, on her own time. Individual results vary. CoreReset does not repair a torn tendon.

Inside CoreReset
Every part of CoreReset was designed around one job: making the hip stabilizers contract again, at home, without help — and without pressing on the tendon.

The muscles that were locked out get worked every day — so the tendon isn’t carrying the load on its own anymore.

Works alongside what you already do.
CoreReset doesn’t replace your pills, your physical therapy or your doctor’s advice — it works on the muscles those treatments were never aimed at. Most women simply add one session a day to their routine.
Most routines for gluteal tendinopathy ask you to do more exercises. CoreReset asks for fifteen minutes in your chair — no movement, no pressure on the tendon.
Do not use CoreReset if you have a pacemaker, defibrillator or other implanted device, if you are pregnant, if you have epilepsy, or on broken or numb skin. If you have a heart condition, recent surgery, a torn tendon, or are being treated for your hip, talk to your doctor first.
If a device is aimed at the muscles nothing else has reached, standing behind it should not be complicated.
Use CoreReset for 90 days. If you don’t feel the difference, you get a full refund — and you can keep the device. Refunds are handled by our US support team within 48 hours.
The 90 days mirror the window the first group was tracked over — the same window in which most of them noticed a real change.
Every device also comes with a 1-year warranty.
Why Starting Sooner Matters
The lockout runs in one direction.
Every month the stabilizers stay quiet, they shrink a little more. Every bit of shrinking puts more load on the tendon. More load means more pain. More pain switches the muscles down further. Which means even less support on the next step.
That is what sits behind what so many women describe as “it just keeps getting worse” — the walk around the block that used to be nothing, the nights you now dread, the walks you’ve quietly stopped taking.
And it is why “rest it and it will settle down” so rarely works out the way it sounds. Resting doesn’t keep the hip where it is. Every month of resting is another month of the muscles going quiet — and a weaker hip to carry into whatever comes next.
The muscles you have today are the most responsive they will be. Every month they go unworked, that changes.

Important — Please Read
CoreReset Is Not Sold on Amazon
CoreReset is only available at trykaviera.com. If it shows up anywhere else, it isn’t the real thing. Here’s what’s going on:
- Copycat “hip stimulators” have appeared on Amazon using the CoreReset name and photos.
- These knock-offs don’t have the Dual-Action program or the butterfly pad made for the outer hip.
- Some are never shipped at all — buyers are charged and receive nothing.
- Unfortunately, real customers have already been caught out this way.
- Kaviera is actively working to get these listings removed.
The genuine CoreReset is sold in one place only: trykaviera.com
From Women Who Had Stopped Expecting Anything to Help

This is the first thing that has ever touched the burning on the side of my hip. About five weeks in I noticed I could sit through a whole movie without shifting. I’m not going to say I’m cured, but I’m doing things I had stopped doing.

I use it every evening in my recliner while I watch TV. After about two months I realized I’d slept through the night on my bad side and hadn’t even noticed. Still have stiff afternoons, but the nights are mine again.

Someone in a gluteal tendinopathy group shared the article and the part about the tendon getting squeezed made more sense than anything I’d been told. No movement, nothing to push through. Took about six weeks. Last Saturday I walked the whole farmers market. My husband noticed I wasn’t limping before I did.

Why it’s not always in stock
The last thing worth knowing is that CoreReset is not always in stock.
It is produced in small batches, and a portion of every batch goes to women already on their daily routine who reorder pads. Whatever remains is released to new customers, first-come, first-served.
When a batch sells out, the next one takes six to eight weeks to arrive, and existing customers are placed ahead of new customers for restocks.
But if CoreReset is in stock, this is an invitation to join the women who are already using it.