Orthopedic Physical Therapist Warns: I've Treated Thousands of Women With Gluteal Tendinopathy. If the Exercises Didn't Fix It, or Made It Worse, Your Muscle Is "Locked Out"

Why glute exercises so often make gluteal tendinopathy worse after 50: a neuromuscular specialist on the hidden "lockout" that keeps the muscle switched off, what he learned when his own wife got worse, and the 15 minute evening ritual that switches it back on first.

The Real Reason Your Tendon Treatments Keep Failing
If you've been managing gluteal tendinopathy for more than six months, doing your exercises religiously, getting the injections, maybe the shockwave, and you're still not meaningfully better: it's not your fault. You didn't do the exercises wrong, and it's not "just your age." I want to share something before your doctor recommends the next round.
The treatment you've been given isn't wrong. It's in the wrong order.
Your physical therapist already knows about the muscle above your tendon. What nobody checks is whether that muscle is actually switched on.
I've spent 26 years as a physical therapist, the last fifteen in hip and neuromuscular rehabilitation, and I've sat across from thousands of women told their hip pain was bursitis, then tendinopathy, then "something to manage."
And for most of those years, when the treatments failed, I wrote one word on their chart.
Tendinopathy.
It sounds like an answer. It isn't. It's what we write when a tendon is breaking down and we don't ask why. A big word that sounds like a solved mystery, handed over with a printout of clamshell exercises and a "see you in three months."
If no one has ever apologized for that, let me be the first. Because what I found when I finally started asking why changed how I practice, and it started in my own house.
The Night It Came Home

Twenty years into my career, my wife Carol, fifty-seven at the time and still teaching full time, started describing the same symptoms I had been filing away on other women's charts for two decades.
Pain on the outside of the hip that pulsed at night. Mornings spent testing the floor before trusting it. One good side to sleep on, and a pillow clamped between her knees like medical equipment.
For three years, I watched her run the same gauntlet my patients ran. First the word bursitis, and a cortisone shot that bought her five good weeks. Then the new word, tendinopathy, and months of loading exercises she did religiously, in our living room, while I pretended not to see her wince. Then shockwave. A TENS unit that ended up in a drawer. A red light panel in the spare room. Collagen powders lined up on the kitchen counter like little jars of hope.
The woman who used to outwalk me started sleeping upright in the recliner, because the bed had become the enemy.
And I am ashamed to admit this part: for two of those years, I treated her the way I had been trained to. The same clamshells and bands I gave every woman who walked into my clinic. And when it hurt more, I told her to push through, and blamed the rest on her age. "Just menopause." "Wear and tear." I treat hips for a living. And I was loading a muscle that couldn't hear me.
The Clue Was Sitting in the Research All Along
The night I finally got angry about it, I did what I should have done years earlier. I pulled the research on lateral hip pain and read it as a husband, not a clinician.
And there it was, in study after study, some of it going back decades: in women with this condition, the gluteus medius, the muscle that stabilizes the hip with every step, is measurably inhibited. Present, but not firing. The scans kept showing everyone the damaged tendon. The research kept whispering about the muscle behind it.
Even the landmark trial on this condition, the LEAP trial published in The BMJ, the one every specialist cites, found that a year after the cortisone shot, women were doing no better than women who had simply waited. We quoted the conclusion and kept injecting the tendon.
The answer was never hidden. We were just never looking where it pointed.
The Guardian That Switched Off

Here is the anatomy they never explain to you. Your gluteus medius is your hip's Guardian. Every time you stand on one leg, and you stand on one leg with every single step you take, it fires to keep your pelvis level and carry the load that would otherwise crush the tendons and the bursa beneath it.
Think of your tendons as the ropes of a suspension bridge, and this muscle as the tower holding them. When the tower stops carrying its share, the ropes don't complain right away. They fray. Slowly. For months.
It doesn't happen overnight. Decades of sitting teach the Guardian to switch off. A woman's wider pelvis asks it to work harder with every step. And then, around menopause, something changes that no one warns you about. Estrogen is one of the signals that keeps muscle strong, and as it falls, muscle starts losing strength. The first to go are the muscles that carry the most weight for their size. Your Guardian holds up your entire pelvis every time you stand on one leg, and nothing in normal life ever trains it. So it weakens first. Silently. No pain at all.
But a Guardian that can't hold the pelvis level lets it drop a little with every step, and the tendon underneath gets pressed against the bone. With every single step, thousands of times a day, the tendon takes another squeeze. That is when the burning starts.
Notice when it hurts. Lying on your side. Crossing your legs. Standing on one leg to step into your pants. Every one of those positions presses the tendon against the bone. If your tendon were simply "old," it would hurt the same all the time. It hurts when it's being crushed.
And here is the cruel part. The moment that tendon hurts, your brain does what brains do to protect a painful joint: it turns the Guardian down even further, like a breaker tripping in a house. Researchers have a name for this reflex: arthrogenic muscle inhibition. When a joint hurts, the nervous system quietly cuts the signal to the muscles around it, to protect it. It was meant to last days. In women with this condition, it never switches back. The muscle is still there. It is simply not being turned on.
So the bursa gets squeezed, that was the first diagnosis. The tendons fray, that was the second. Two labels. One cause. A tower that stopped holding.
The Cycle That Keeps You Stuck

From there, the trap closes quietly. The hip hurts, so you move less. Moving less switches the Guardian down further. A weaker Guardian loads the tendon more. More load, more pain, less movement. Around and around, while the calendar pages fall.
You recognize the life this builds. Getting out of a chair becomes a small negotiation. The stairs become a strategy. You start saying no to things, the walk, the trip, the garden, in ways so gradual that nobody around you notices the shrinking.
And this is usually where someone sells you the hormone story: it's menopause, your tendons are losing collagen. That part is true, but not the way they tell it. The drop in estrogen didn't attack your tendon first. It quietly weakened the muscle that protects it. That was the match. What's burning now is something else.
A tendon doesn't break because it's fifty-five. A twenty-five-year-old's tendon would burn too if you pressed it into the bone thousands of times a day, with every single step. You can feed it collagen. You can bathe it in red light. You can inject it. Tomorrow it gets crushed again.
And you don't put out a fire by taking back the match. You can't undo menopause, and you don't need to. Women on full hormone therapy get this pain too. Raising your estrogen today does not unlock a muscle your brain switched off years ago. The lock isn't hormonal. It's in the wiring between your brain and your Guardian.
Estrogen lit the match. The switched off Guardian is the fire. Millions of women go through menopause and never develop this pain, because their Guardian stayed on duty. And no capsule can switch a muscle back on. That is not a nutritional problem. It is an electrical one.
The hormones explain how it started. The switched off muscle explains why it never heals.
Why Nothing You Tried Ever Worked

Now look back at your own gauntlet through this lens, and watch every failure explain itself.
The loading program. Clamshells, bridges, band walks, done religiously while your friends just went for walks. It demands strength from a muscle your brain has switched off. You cannot train a muscle that isn't firing. It was the right program, in the wrong order. You were asked to build strength in a muscle that hadn't been switched back on yet.
Here is what actually happens when you lie on your side and do a clamshell. You ask the Guardian to fire. Your brain says no. So a smaller muscle at the front of your hip does the work instead, and it pulls the band on the outside of your thigh tight across the bone, right over the sore tendon. Every rep you did for the muscle squeezed the tendon instead. That's why you were sorer the next morning. It's like pressing the gas with the handbrake on: the harder you push, the more the tendon takes the strain. You weren't doing them wrong. You were doing them perfectly, on a muscle that was locked out.
And that's why the videos online won't save you either. They show the right exercises. For a muscle that's switched on.
The cortisone injection. Three to six good weeks, just long enough to give you hope, because it calms the area while doing nothing about what crushes it every night.
The shockwave. Expensive, uncomfortable, and aimed at the victim. It asks a fraying tendon to remodel while the tower keeps leaning on it.
The red light panel. It can warm the skin. But the light fades within a few millimeters, and even if it reached the Guardian, light can't make a muscle contract.
The collagen powders and hormone supplements. A capsule has to survive your stomach and your bloodstream, and maybe, months later, something reaches your hip. Even if it did: you cannot rebuild a tendon that is still being crushed every single night. Hope, swallowed daily.
Every one of these options works around the lockout. None of them works on it. You didn't fail the treatments. The treatments failed the mechanism.
It's Not a Tendon Problem. It's a Switch Problem.
Here is what took me twenty years too long to see, and what I now tell every woman who sits in my office.
Ask a hundred experts how to fix lateral hip pain and a hundred will hand you the same answer: exercises for the muscle. Not the tendon. Everyone in medicine already knows, deep down, that the tendon is simply what breaks when the muscle stops doing its job. The tendon is the consequence. The muscle is the cause. That is why every treatment plan ever written ends with a page of exercises.
Your physical therapist was right about the muscle. And right that it has to get stronger. What nobody told either of you is that the order matters.
So the cure was never in doubt. The muscle must be retrained. The only question nobody could answer is how, because a muscle your brain has switched off cannot be trained with exercises. You cannot clamshell your way into a contraction that isn't happening.
So the science now says: reverse the order. First, switch the muscle back on, with zero load on the tendon. Then let it get stronger, contraction after contraction, still without loading the tendon. That's exactly the job your exercises were trying to do, done in the right order.
The Discovery That Changed Everything
The technology that breaks this cycle is not new, and it is not experimental. It has been used in rehabilitation clinics and by professional sports teams for over 40 years. It's called NMES: neuromuscular electrical stimulation.
Every treatment you tried asked the muscle to fire. NMES does the opposite. It sends targeted pulses deep into the tissue and makes the Guardian contract, bypassing the brain's off switch entirely. The muscle cannot say no. Contraction after contraction, the pathway between brain and muscle rebuilds itself, until the Guardian starts showing up on its own again.
If you're thinking of the TENS unit in your drawer, it's a different machine. A TENS works on the nerves just under your skin to cover up the pain signal. You feel a tingle, and the muscle doesn't move. Turn it off, and the pain is back. NMES reaches the nerve that drives the muscle and makes it contract. One masks the pain. The other wakes the Guardian.
5 to 8mm deep
The Guardian stays asleep.
30 to 50mm deep
Forces it to fire.
The deep stabilizers of your hip sit thirty to fifty millimeters below the skin. Surface stimulation stops at eight.
When I first watched it work on Carol's hip, after three years of watching everything else fail, I understood why clinics guard this tool so casually. It was never a secret. It was just never offered to women like her.
The Treatment Reserved for Clinics and Pro Athletes
There was, of course, a catch. Clinical NMES means appointments. A machine the size of a nightstand. Sessions billed one by one, weeks of them, assuming you can find a clinic that offers it for this condition at all. Professional athletes get it daily, between practices, as a matter of routine. A 56 year old woman with a hip that hurts at night gets a printout of clamshells.
I called colleagues. The answer was always the same: yes, it works, yes, we use it, no, there's no practical way to prescribe it for months of daily use at home.
Carol needed the clinic's technology without the clinic. That device did not exist on any shelf I could find. So I went looking for the people building it.
So We Brought the Clinic Into the Living Room
After months of searching and testing, I found a small engineering team working on exactly this: an at home NMES device, calibrated not for athletes' quads but for the deep stabilizers of the hip, the exact thirty to fifty millimeter depth where this lockout lives. It's called the CoreReset NMES Pro™, and I put my name behind it only after Carol had used it for twelve straight weeks.
Every 15 minute session does two things:
Phase A: Load Offload. Gentle, rhythmic contractions rebuild the suspension around your hip, taking your body weight off the tendon so it can finally heal.
Phase B: Reeducation. Contraction after contraction, the pathway between your brain and the Guardian rebuilds itself. Within the first weeks the muscle starts answering again, by day 60 it fires on its own, and every session keeps making it stronger, with no load on the tendon.
That's what Dual-Action NMES means: every pulse contracts the muscle, then releases it. Work, rest. Work, rest. The muscle does its job again, and the tendon underneath never gets loaded.
Fifteen minutes a day. Six programs, twenty intensity levels. It switches itself off when the session is done. Most women run it while watching the evening news.
See If CoreReset Is Right For YouWhat Happened to My Wife

The first session, Carol felt something she hadn't felt in years: a deep, slow pulse inside the hip. Not the surface buzz of her old TENS. The muscle itself, contracting. Her word for it was "weirdly emotional."
By the end of week one, the pillow between her knees stayed in place all night instead of ending up on the floor. By week three, she slept on her forbidden side and woke up without the flare. Around week six, she stood up from the car without the little negotiation I had watched a thousand times. If you've lived with this condition, you know that sentence is everything.
At 60 days she dropped to maintenance, fifteen minutes on Monday, Wednesday, Friday. The Guardian carries her the rest of the week. Last spring she sent me a photo while I was at the clinic: crouched in her garden at golden hour, both hands in the tomato plants. Two years earlier she couldn't lie flat in her own bed.
The tendon got what it had needed all along: its bodyguard back.
What to Expect in Your First 60 Days

Day one: a deep, slow pulse inside the muscle in the very first session. By the end of it, the side of your hip feels lighter, as if something finally let go. Many women sleep a little easier that same night.
Week one: you wake up less. The pillow stays where you put it. Getting out of bed takes one move instead of three.
Weeks two to three: you roll onto your forbidden side without the spike that used to wake you, and fall asleep there.
Weeks four to six: you stand up from the car without negotiating. The stairs stop being a strategy. You catch yourself walking to the mailbox just because you can.
Day 60: the Guardian fires on its own. Most women no longer need it every day: many keep it on the nightstand and use it a couple of times a week, or whenever the hip starts to talk again. It's yours. No refills, no appointments, no next shot.
How Does It Actually Work? (It Takes 15 Minutes)
Position the device over your hip. Press the button. Sit back. It runs the session and switches itself off. No gels to mix, no appointments, no learning curve. If you can operate a television remote, you can run your own protocol.
Start Your Protocol TonightThen Her Walking Group Found Out
Carol talks. It's one of the reasons I married her. Within a month, the women in her walking group, the same group she had quietly quit two years earlier, wanted to know what changed. Then their sisters called. Then their book clubs.
I started getting emails forwarded from women I had never met, all telling some version of the same story: the labels collected over the years, the drawer full of failed devices, the first night of real sleep. That is when I decided this page needed to exist. Not every woman has a rehab specialist at the dinner table.
What Women Are Experiencing
I will not pretend every story is Carol's story, and anyone who promises you that is selling something. But certain sentences now repeat so often, from so many women, that I can tell you the order they arrive in. Sleep first. Then mornings. Then the day you have to think, genuinely think, to remember which side was the bad one.



The Letters Started Arriving
Since this page went live, I have been told three times, politely and through lawyers, that it would be better for everyone if it came down. The device has no billing code, they say. It is not part of any approved protocol, they say.
An attorney friend read the letters and laughed. Letters like these are never about safety. They are about revenue. When a woman cancels her third injection appointment because she is holding a device that costs less than one copay, someone, somewhere, stops getting paid.
I recognize the playbook because I spent 26 years inside it. The loop is the business model: manage the tendon, repeat the tendon, schedule the tendon. They do not want you out of the loop, because the loop is where the money lives.
Then a distributor that rents red light panels to clinics called the company directly. Their complaint was almost honest: at this price, they said, you are destroying the perceived value of light therapy.
They are right. It is being destroyed. Because perceived value never switched a single muscle back on.
That is why the current batch is still sold directly, at a fraction of the clinic price, while units last. And I will be straight with you about the future: the company keeps sourcing components and shipping orders, but if one of these letters ever lands in the wrong courtroom, this page disappears along with the stock.
>>> CHECK IF CORERESET IS STILL IN STOCK <<<The Choice That Will Define Your Next Decade
Right now, you're standing at a fork in the road.

Path #1: Keep doing what you're doing. Another round of exercises on a muscle that can't hear them. Another shot that wears off a little faster than the last. Another night half on your back, the pillow sliding out from between your knees. Saying "maybe next time" to the walk, the trip, the floor with the grandkids. And every month, the Guardian stays off duty a little longer.
Path #2: Switch the Guardian back on first. Fifteen minutes in the evening, lying down, while the muscle does the work your exercises were trying to do. The pelvis holds level again. The squeeze comes off the tendon. Your nights come back first. Then your walks.
Same hip. Same starting point. The only thing that changes is which path you take tonight.
My Honest Recommendation
You have already spent the money and the years on everything that works around the problem. You know the ledger by heart: the injections that bought a few weeks, the shockwave, the TENS, the red light, the powders. All of it aimed at the victim. None of it at the cause.
CoreReset costs less than a single copay on the treatments that failed you, because the team behind it sells directly on this page instead of through clinics. It is not for everyone. If you have a pacemaker or an implanted electrical device, if you are pregnant, or if you would place it over an active tumor or a known blood clot, do not use it. Everyone else can try it the way medicine should always be tried: with the risk on us, not on you.
Try It Risk Free Tonight

I told the company I would put my name on this page under one condition only: the guarantee has to outlast your skepticism. And after everything you've been through, you have earned the right to be skeptical.
Use CoreReset for 90 days. Fifteen minutes a day. If the lockout doesn't break, if your nights don't change, if your mornings don't get easier, you're covered by our 90-day money-back guarantee.
You either wake the Guardian, or it costs you nothing.
The Questions Women Ask Me Before They Start
I've done tendon loading for months. Why would this be any different?
Because loading demands strength from a muscle that isn't firing, which is why it exhausted you. The exercises weren't wrong. They came too early. CoreReset forces the Guardian to contract first, rebuilds the pathway between brain and muscle, and keeps strengthening it session after session, with no weight on the tendon. The strength your exercises were chasing, in the order your muscle can actually accept it.
What about shockwave, red light therapy, or another injection?
All three work on the tissue at the surface or on the tendon itself, while the muscle that failed stays switched off. Wake the bodyguard first. The tendon finally gets the quiet it needs to heal.
How is this different from the TENS unit in my drawer?
Depth and purpose. TENS distracts surface nerves a few millimeters down. The Guardian sits thirty to fifty millimeters deep, and TENS literally cannot reach it. One masks the pain. The other wakes the muscle.
Can't I just buy a cheap muscle stimulator online?
Most of them are TENS units, or generic pads made for thighs and abs. They either stay at the surface or were never set up for a muscle thirty to fifty millimeters deep on the side of your hip. CoreReset's butterfly pad is shaped for that spot, and each session runs the program and switches itself off. You don't have to guess the settings.
Is it safe? Any side effects?
NMES has been used in clinical rehabilitation for over 40 years. The pulses are gentle and drug free, with no interactions with your prescriptions. If you have a pacemaker or any implanted electrical device, if you're pregnant, or if you'd place the pads over an active tumor or a known blood clot, this isn't for you. Otherwise, it's safe for virtually everyone.
How fast will I feel it?
The deep pulse, the very first session: a slow contraction inside the muscle, nothing like a surface buzz. Most women report their first real nights of sleep inside the first two weeks. For most women the pathway is back within about 60 days. The guarantee lasts 90, so you have more time than you need to feel it for yourself.
My physical therapist already tried e-stim on me. It only helped for a few hours.
Most clinic e-stim is used for pain, or for ten minutes twice a week, and rarely placed on the Guardian itself. That calms the pain for a while and stops there. CoreReset is set up to make the gluteus medius contract, right where it sits on the side of your hip, every day. The goal isn't a few quiet hours. It's a muscle that switches back on and stays on.
Will it hurt? My hip is already so tender.
You start at the lowest of 20 levels. It feels like a deep, rhythmic pulse inside the muscle, not a shock. You turn it up only when you're ready, and one button turns it down or off. If the area is very tender, you simply stay low.
I can't even do the exercises anymore. Can I still use it?
Yes. That's exactly who it's for. You don't lift your leg, balance or move at all. You sit or lie down, and the muscle does the work while you rest.
Will I have to use it forever?
No. Daily for the first 60 days, while the Guardian comes back online. After that, most women use it now and then, the way you'd keep any muscle in shape. And unlike a shot or a PT visit, you only pay once.
What if it doesn't work for me?
Then you shouldn't pay for it. Most women feel the deep pulse in the very first session and notice their nights changing within the first few weeks. But every hip is different, so you have 90 days to try it at home, longer than the 60 days most women need, and you're covered by our 90-day money-back guarantee.






Stop Loading a Locked-Out Muscle. Wake the Guardian First.
Start Your Protocol Tonight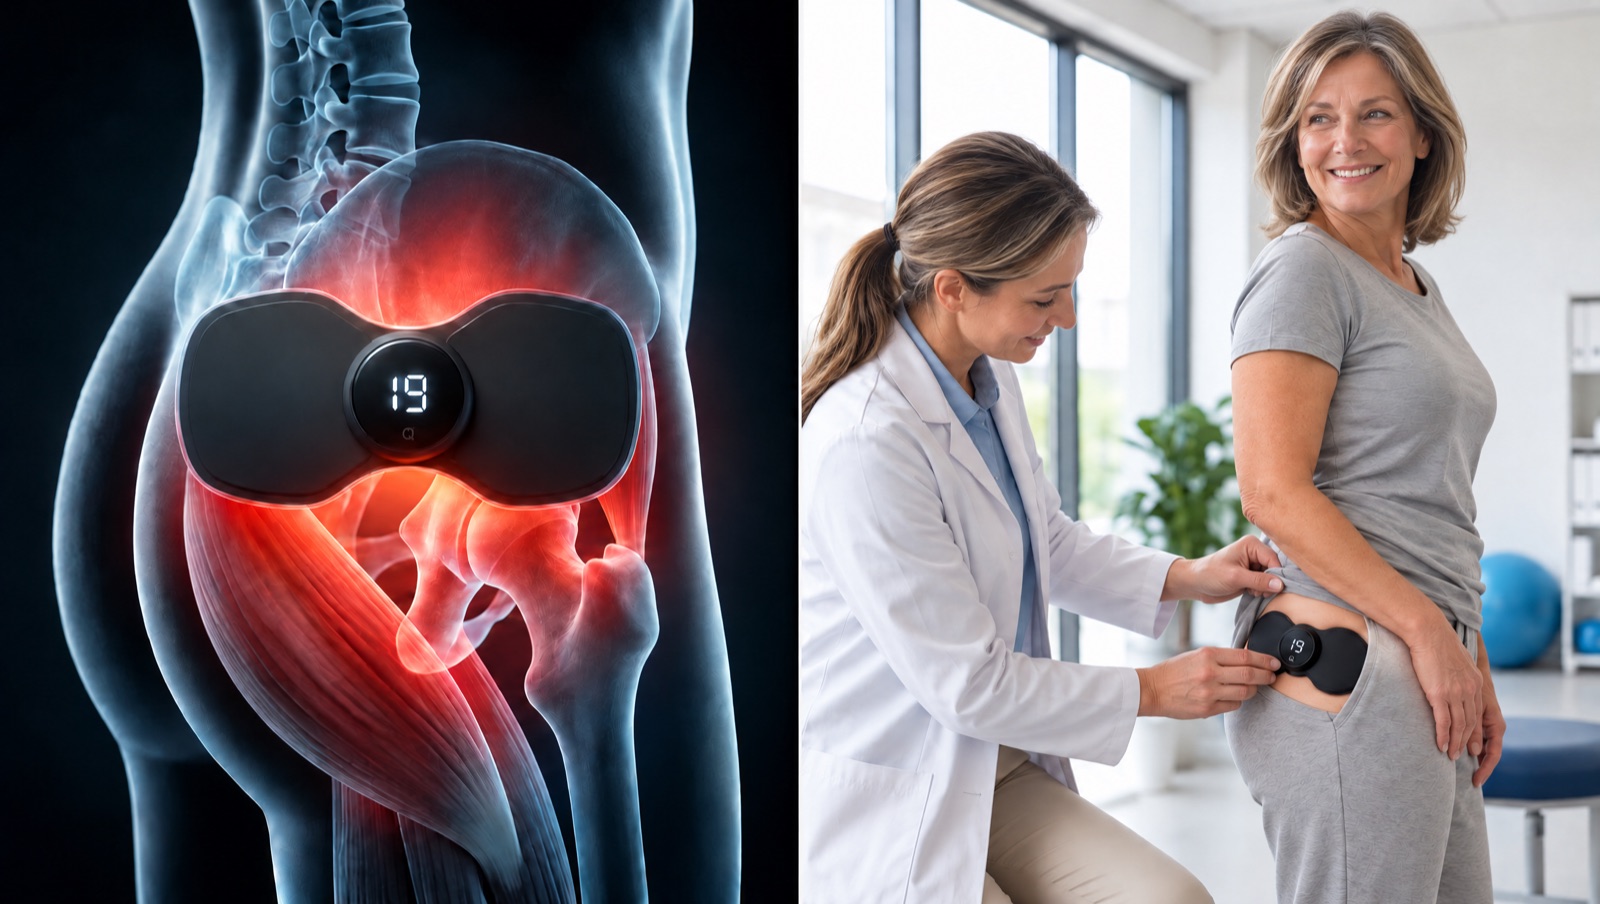
- Reaches the Guardian at 30 to 50mm deep
- 15 minutes a day, at home
- Drug free, 40 years of clinical use
- 90 day money back guarantee